TRENDING

Sunday, 15 November 2026
----------------------
5 Jumada Al-Thani 1448 AH
Zimbabwe's remarkable progress in combating HIV/AIDS is now under threat, as a generation unfamiliar with the epidemic's devastating peak shows signs of complacency. This shift, coupled with economic pressures and funding volatility, puts hard-won gains at risk.
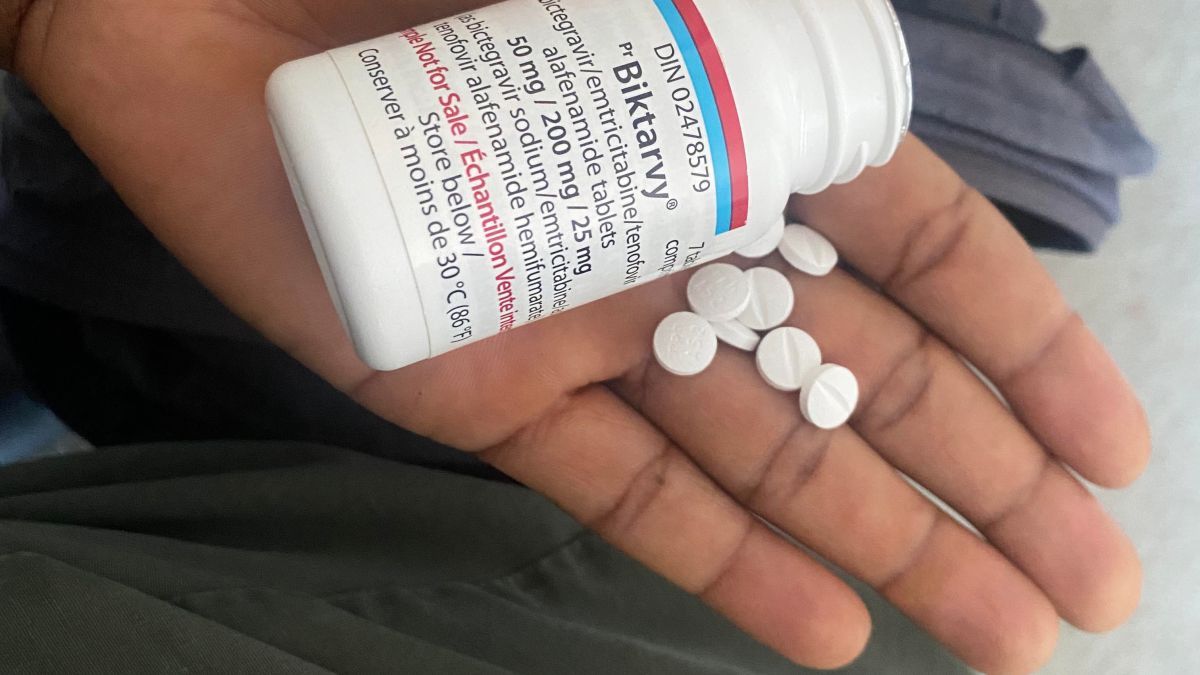
Zimbabwe, a nation that once bore the brunt of the HIV/AIDS epidemic, is witnessing a concerning trend: a potential reversal of its significant gains in HIV prevention among young people. While the country dramatically reduced annual new infections from 79,000 in 2010 to 15,000 in 2023, and infections among 15-24 year olds dropped from 27,000 to 4,400 in the same period, healthcare workers and public health advocates are sounding alarms. They point to a generation that, having grown up with effective antiretroviral treatment (ARVs) and prevention tools like PrEP and condoms, may underestimate the virus's severity, leading to complacency and a potential resurgence of infections.
The apparent shift in Zimbabwe's HIV landscape is a complex interplay of global health funding, national governance, pharmaceutical advancements, and societal memory. At its core, the transformation of HIV from a death sentence to a manageable chronic condition has fundamentally altered the power dynamic between the virus and human agency. ARVs and PrEP represent a monumental scientific victory, shifting the power from the pathogen to medical intervention. However, this medical triumph inadvertently creates a new challenge: the erosion of collective memory regarding the epidemic's initial, devastating phase.
Globally, the fight against HIV/AIDS has been heavily reliant on international funding, particularly from nations like the United States. This dependency means that shifts in donor priorities, domestic political changes in funding countries, or even global economic downturns can directly impact the availability of life-saving drugs, testing kits, and prevention programs in recipient nations. The reported disruptions to US-funded HIV programs in Zimbabwe in March 2025 underscore this precarious reliance. When external funding falters, the power to sustain public health initiatives falls squarely on the shoulders of national governments, often in economies already strained.
Within Zimbabwe, the government's capacity to decentralize services—taking PrEP, testing, and treatment beyond major hospitals to communities, including informal mining sites—is a crucial lever. This decentralization aims to empower individuals by making services accessible, but its effectiveness is contingent on consistent resource allocation, robust supply chains, and a committed healthcare workforce. The challenge is not just medical but logistical and administrative, requiring a strong, sustained political will that often competes with other pressing national priorities.
Furthermore, the pharmaceutical industry holds significant power. While the development of long-acting injectables like lenacapavir promises revolutionary prevention, their widespread accessibility and affordability in low-income settings like Zimbabwe remain a critical hurdle. The power to innovate is concentrated, but the power to distribute equitably is diffused and often constrained by economic realities and intellectual property rights. This creates a two-tiered system where advanced prevention options might be available, but not necessarily to those who need them most.
Finally, the power of social narrative and stigma cannot be overstated. Healthcare professionals like Shaun Moyo observe a generational disconnect, where the lived horror of the 1990s is absent from the collective consciousness of today's youth. This gap allows for a dangerous complacency, where the perceived
Zimbabwe's progress is threatened because a younger generation, unfamiliar with the epidemic's peak, may underestimate HIV's severity. This complacency, combined with economic pressures, funding disruptions, and communication gaps in prevention efforts, puts hard-won gains at risk.
Global funding, particularly from countries like the United States, has been crucial for Zimbabwe's HIV programs, including ARV distribution and prevention services. Disruptions to this funding can severely impact the country's ability to sustain these vital health initiatives.
Healthcare providers are adopting new strategies, including decentralized services, mobile clinics, and pop-up health services in places young people frequent. They are also using peer educators and youth-friendly communication to address stigma and provide practical information without judgment.
Source referenced: ALJAZEERA
This brief was synthesized by our Editorial Engine and reviewed by The Ground Narrative team.


